Explore expert articles, clinical guides, safety standards, and product updates from NOA Medical Industries.
Choosing the right Acute Care Hospital Beds in 2026 requires more than comparing prices or digital features. These beds support patients needing rapid assessment, frequent repositioning, respiratory care, and continuous monitoring. A practical decision begins at the bedside. Can the bed turn smoothly in a crowded room? Can nurses adjust its height without leaving the patient? Does the frame remain stable during transfers? These details influence safety, workflow, and patient dignity.
This guide examines essential criteria, including safe working load, low-height access, side-rail design, mattress compatibility, and infection-control surfaces. It also considers electrical reliability, battery backup, alarm usability, and compatibility with monitoring equipment. Clinical engineering teams should review service records, warranty terms, spare-parts access, and staff training requirements. Nurses often reveal weaknesses that product brochures hide. A quiet wheel matters during a night shift. A confusing control panel may delay care. No checklist is perfect.
Reliable decisions should draw from recognized standards, manufacturer documentation, independent clinical evaluations, and feedback from multidisciplinary hospital teams. An intensive care unit may need advanced positioning and monitoring integration. A general medical ward may prioritize durability and easy cleaning. Costs deserve attention, but the cheapest bed can become expensive through repairs, downtime, or preventable workflow problems. Some recommendations may remain uncertain because performance varies across suppliers and clinical settings. That uncertainty deserves honest review. By weighing patient needs, staff experience, verified specifications, and long-term support, hospitals can make a safer and more defensible procurement choice for 2026.
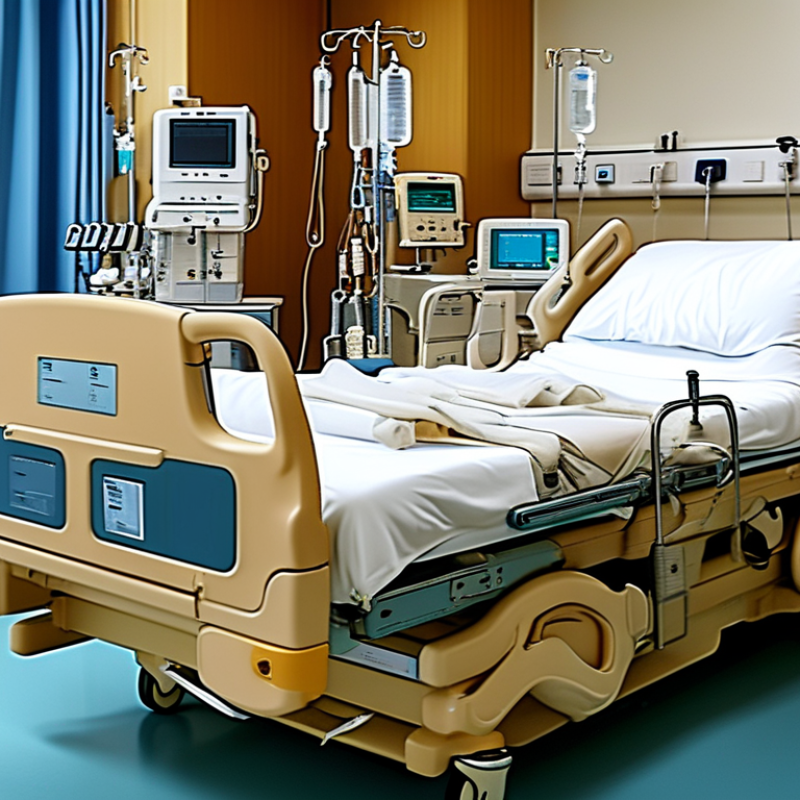
Choosing acute care beds in 2026 starts with clinical risk, not upholstery.
IEC 60601-2-52 specifies safety requirements for electrically operated medical beds.
These include patient support, movement, access, load limits, and entrapment prevention.
Use the standard as a design filter.
Verify mattress dimensions, side-rail gaps, emergency lowering, wheel brakes, and control placement.
A bedside test often reveals problems that brochures hide.
Define acuity levels locally before comparing bed features.
A low-acuity patient
may need basic positioning and safe transfers.
Moderate acuity
can require frequent repositioning, pressure injury prevention, and easier nursing access.
High acuity
may require rapid emergency positioning, continuous monitoring, and stronger support for lines and devices.
Critical care
demands reliable articulation, CPR positioning, patient handling, and equipment compatibility.
These labels are not universal. Your hospital’s scoring system must guide selection.
The WHO Global Patient Safety Report 2024 estimates that one in ten patients experiences harm during healthcare, with more than half considered preventable.
Bed-related risks deserve practical attention. Measure twice. Observe transfers at night, not only during demonstrations.
The OECD Health at a Glance 2023 reports an average of 4.3 hospital beds per 1,000 people across member countries, but bed numbers alone do not define readiness.
Review falls, pressure injuries, average patient weight, staffing patterns, cleaning time, and emergency response data.
Reality changes. Procurement teams should revisit their assumptions before final approval.
Choosing an acute care bed in 2026 requires more than counting motors. A four-motor design usually supports independent height, backrest, thigh, and tilt adjustments. That control can help nurses position patients without repeated manual lifting. A 30° backrest elevation is also clinically meaningful. The AHRQ National Healthcare Quality and Disparities Report links safer positioning and pressure-injury prevention with better inpatient care processes. However, 30° is not a magic setting. Patient anatomy, respiratory status, sacral pressure, and clinical orders still matter.
A safe working load of at least 500 pounds deserves careful inspection. This figure includes the patient, mattress, pumps, bedding, and attached equipment. It is not the patient’s maximum weight. IEC 60601-2-52 addresses essential safety requirements for medical beds, while facility buyers should also review tested load limits, rail clearances, braking performance, and service records. A bed may look strong. It may still fail routine checks.
Tips: Ask for load-test documentation, not marketing language. Test the bed with a mattress, oxygen cylinder, and monitor attached. Confirm the lowest height, because transfers happen beside real floors, not showrooms. Verify that the 30° position is visible and repeatable. Staff feedback should influence selection, although it can be inconsistent. That is worth admitting. Pilot several beds during busy shifts, then record repositioning time, alarm usability, and cleaning effort before purchasing.
Choosing an acute care hospital bed in 2026 requires more than checking weight capacity and height adjustment. Patient safety begins with reviewing current FDA guidance on bed entrapment risks. Examine the mattress, side rails, headboard, and footboard as one system. Dangerous gaps can appear when parts do not fit correctly.
Measure the spaces around the mattress and rail areas. Watch for shoulder, neck, chest, and head entrapment zones. A bed may pass a factory inspection but still create hazards after repeated cleaning or mattress replacement. Compatibility matters. So does maintenance.
IEC 60601-1 provides a key reference for basic electrical safety and essential performance. Confirm protection against electric shock, stable grounding, cable durability, and reliable operation of motors and controls. Test the bed with accessories installed, not only in its ideal configuration. Ask for test reports, risk assessments, instructions, and service records from qualified suppliers.
Nurses should be able to lock the casters quickly. Patients should not struggle with controls. Alarm sounds must be clear without becoming disruptive. These details are easy to overlook.
FDA guidance and IEC 60601-1 support safer decisions, but neither replaces clinical judgment. Review the bed in realistic rooms, with actual mattresses and patient-care routines. A checklist helps. It is not enough. Safety findings should be documented, discussed, and reviewed when equipment or patient needs change.
| Evaluation Dimension | Evidence-Based Requirement | What to Verify Before Purchase | Recommended Acceptance Evidence | Priority |
|---|---|---|---|---|
| Regulatory and standards scope | IEC 60601-1 addresses basic safety and essential performance for medical electrical equipment. Medical beds also require review of the applicable particular standard, typically IEC 60601-2-52, and any national adoption. | Confirm the exact standard edition, national deviations, classification, intended environment, and whether accessories are included in the assessment. | Current, product-specific test reports or certificates from a competent testing organization, plus a documented standards matrix. | Critical |
| Patient entrapment prevention | The FDA’s hospital-bed entrapment guidance evaluates hazardous openings around the mattress, bed frame, and bed rails. Entrapment risk depends on the complete bed system, not the rail alone. | Assess all FDA-identified entrapment zones with the specified mattress, rails, headboard, footboard, and positioning accessories installed. | Documented dimensional assessment, configuration-specific test results, risk analysis, and instructions identifying approved mattress and rail combinations. | Critical |
| Mattress and frame compatibility | A mattress that is too narrow, too short, too soft, or incorrectly positioned can create gaps and alter entrapment performance. Pressure-redistribution mattresses may also change deck height and patient positioning. | Match mattress dimensions, thickness, stiffness, weight limits, articulation limits, and attachment method to the bed manufacturer’s approved configuration. | Compatibility list, dimensional drawings, maximum patient and mattress loads, and testing performed with the specified mattress type. | Critical |
| Bed-rail design and use | Bed rails can reduce falls in selected situations but can also create entrapment, climbing, or injury hazards. Rail use should follow an individualized clinical assessment and facility policy. | Check rail locking, unintended release resistance, pinch points, visibility, transfer clearance, and compatibility with the mattress and patient population. | Usability and mechanical test records, rail-position instructions, staff training materials, and a documented clinical risk-assessment process. | Critical |
| Electrical safety | IEC 60601-1 covers hazards such as electric shock, excessive temperatures, mechanical risks, and essential performance for applicable medical electrical equipment. | Verify protective earth or double-insulation design, leakage-current testing, dielectric strength, power-cord protection, accessible connector safety, and operation during abnormal conditions. | Standards-based test report, electrical safety test procedure, service-test limits, and preventive-maintenance requirements. | Critical |
| Emergency functions | Acute care beds should support rapid clinical response through functions such as emergency backrest release, CPR positioning, accessible controls, and safe lowering where specified by the design. | Time and observe emergency operation with mains power available and unavailable, while checking unintended movement, line clearance, and staff access. | Functional test protocol, battery-backup specification, alarm behavior, emergency-use labeling, and documented clinical simulation results. | Critical |
| Safe working load | The safe working load must account for the patient, mattress, bedding, pumps, monitors, and other equipment. Patient weight alone is not the total load. | Compare the facility’s maximum anticipated total load with the stated safe working load and verify whether loads differ by bed position or accessory configuration. | Clear load-labeling, structural test documentation, overload warnings or controls where applicable, and an accessory load schedule. | Critical |
| Fall and transfer risk | A low position can reduce the potential severity of a fall, while an adjustable height can support transfers and caregiver ergonomics. No single bed position is appropriate for every patient. | Confirm usable height range, stable braking, transfer clearance, control accessibility, and whether the lowest position is available during power loss. | Measured height and stability data, brake tests, transfer-use evaluation, and documented fall-prevention workflow. | High |
| Backrest and articulation safety | Powered articulation can affect shear, sliding, tubing tension, patient posture, and gaps between body-support surfaces. Movement must remain controlled throughout the intended range. | Check anti-shear or profiling behavior, movement speed, pinch and crush points, pendant controls, stop functions, and line-management clearance. | Range-of-motion data, mechanical safety tests, clinical usability assessment, and instructions for positioning lines and tubes. | High |
| Infection prevention and cleanability | Smooth, sealed, and accessible surfaces can support effective cleaning. Cleaning agents, contact times, and repeated disinfection can damage materials if they are not approved for the bed. | Inspect seams, joints, casters, mattress covers, control interfaces, drainage areas, and removable components for soil traps. | Validated cleaning instructions, chemical compatibility data, material-care limits, and infection-prevention review of the complete bed system. | High |
| Caster, brake, and transport performance | The bed should remain stable during care and move predictably during transport. Braking and steering performance are especially important on ramps, thresholds, and uneven surfaces. | Test central locking, directional steering, cornering, threshold crossing, ramp use, push forces, and stability with the maximum permitted load. | Transport test results, brake-maintenance limits, wheel inspection criteria, and a defined pre-use safety checklist. | High |
| Alarm, control, and battery management | Controls and alarms should communicate clearly without encouraging unsafe bypassing. Battery-supported functions must remain available for the duration specified by the manufacturer. | Verify audible and visual alarm clarity, control lockout, caregiver/patient control separation, battery status indication, charging behavior, and fault notification. | Human-factors evaluation, alarm test records, battery endurance data, replacement criteria, and staff training documentation. | High |
| Risk management and post-market support | Safety depends on foreseeable misuse, maintenance, accessories, user training, and incident feedback. A risk-management file should address the complete intended-use system. | Review hazard analysis, residual-risk controls, field corrective-action history, spare-parts availability, service response, and software or firmware update controls where applicable. | Risk-management summary, preventive-maintenance schedule, service manual, training plan, complaint process, and traceable corrective-action records. | High |
Note: FDA entrapment guidance is a U.S. regulatory guidance document rather than a universal substitute for applicable laws or standards. IEC 60601-1 is the general medical electrical equipment standard; bed-specific requirements should also be assessed against the applicable edition of IEC 60601-2-52 and national requirements. Final acceptance should be based on the exact bed, mattress, rail, accessory, and intended-use configuration.
Choosing acute care beds in 2026 requires more than load ratings and electronic functions. Infection control should guide the evaluation. CDC practices emphasize hand hygiene, environmental cleaning, and equipment disinfection between patients. Ask whether staff can reach every surface without moving heavy parts. Inspect mattress seams, rail joints, casters, handset buttons, and under-bed frames. Dirt hides there. It often does.
IPX4 protection means the bed enclosure resists water splashes from all directions. It does not mean waterproof or safe for immersion. This distinction matters during bathing, spill response, and routine wipe-downs. Request test documentation, then compare it with the hospital’s cleaning process. Disinfectants, contact time, spray pressure, and repeated use may affect seals and controls. A bed can pass a water test yet remain difficult to clean. That is the uncomfortable gap.
Use CDC-aligned observation rounds to assess real performance. Watch staff clean a bed after discharge, including the mattress platform, rails, cables, and adjustment controls. Check whether surfaces dry quickly and whether equipment can be dedicated to isolation rooms. Keep electrical connectors protected and inspect damaged covers immediately. Training matters, too. A perfect design fails with rushed cleaning. I would also record missed areas, not hide them. Those findings can improve purchasing criteria, maintenance schedules, and bedside audits.
No checklist replaces clinical judgment.
Choosing acute care hospital beds in 2026 requires more than comparing purchase prices. During ward evaluations, I have seen a low quote become expensive after delivery, setup, training, and repairs. Calculate total cost across seven years. Include mattress compatibility, replacement batteries, preventive maintenance, software fees, and disposal. Ask for a written ownership model, not a promotional estimate. This matters.
Battery life deserves testing under realistic clinical pressure. A bed may perform well in a showroom but weaken during repeated height adjustments, transport, and emergency use. Request cycle-test data, charging times, and alerts for declining capacity. Nursing teams should trial the bed during a full shift. Observe cable reach, brake access, and alarm audibility beside oxygen equipment. Our first evaluation missed battery recovery after frequent repositioning. Test it live.
Warranty terms reveal the supplier’s operational confidence. Check coverage for actuators, control panels, batteries, labor, and response times. A short warranty can distort total cost. EHR integration needs equal scrutiny. Confirm data standards, field mapping, user permissions, audit logs, cybersecurity controls, and downtime procedures. Integration should reduce duplicate charting without creating unsafe automation. Ask staff to test admission, bed-status updates, and correction workflows in a sandbox. If nurses need workarounds, the system is not ready.
Anonymous market benchmark comparing representative acute-care bed configurations by estimated purchase cost, battery runtime, warranty coverage, and EHR integration readiness.
Lower total cost and longer battery life improve operational value. Warranty scores represent standard coverage duration, while EHR integration is rated on a 0–100 readiness scale covering network connectivity, data export, device identification, and workflow compatibility. Actual pricing and integration performance should be validated through current hospital quotations and technical trials.
Start with clinical risk, not upholstery. Define low, moderate, high, and critical acuity locally. Labels vary.
Check patient support, movement, access, load limits, and entrapment prevention. Use IEC 60601-2-52 as a design filter.
Test it with the actual mattress and accessories. Observe transfers at night, not only during demonstrations. Small problems appear then.
Examine the mattress, rails, headboard, and footboard together. Measure gaps near the head, neck, chest, and shoulders.
Incorrect dimensions can create dangerous spaces. Recheck after mattress replacement, repeated cleaning, and maintenance. Factory approval is not enough.
Confirm grounding, shock protection, cable durability, motors, and controls. Test emergency lowering and CPR positioning under realistic conditions.
Staff should reach rails, seams, casters, buttons, cables, and under-bed frames easily. Dirt hides there. It often does.
IPX4 resists water splashes from all directions. It is not waterproof or suitable for immersion. Do not overread the rating.
Watch staff clean a discharged patient’s bed. Check drying time, hidden surfaces, connectors, and adjustment controls. Record missed areas.
Review falls, pressure injuries, patient weight, staffing, cleaning time, and emergency response data. Revisit assumptions. They may be wrong.
Choosing the best Acute Care Hospital Beds in 2026 begins with matching bed functions to clinical needs, patient acuity, and applicable IEC 60601-2-52 requirements. Hospitals should compare four-motor adjustment systems, reliable 30° head-of-bed elevation, and safe working loads of at least 500 pounds to support diverse patient populations. Safety evaluations should include compliance with FDA bed-rail entrapment guidance, IEC 60601-1 electrical safety principles, dependable locking mechanisms, and clearly accessible controls for caregivers and patients.
Infection control is equally important. Select beds with smooth, easy-to-clean surfaces, designs that minimize hidden contamination points, and suitable IPX4 protection for routine cleaning environments, while following CDC-recommended disinfection practices. Finally, assess total cost of ownership rather than purchase price alone. Battery endurance, preventive maintenance, warranty coverage, replacement-part availability, and secure EHR integration can significantly affect long-term value. A structured comparison using these criteria helps hospitals improve patient safety, workflow efficiency, durability, and financial performance.
